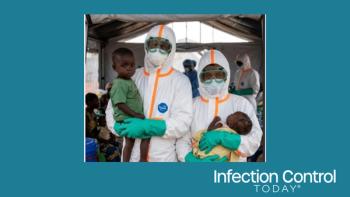
High contact follow-up rates suggest progress, but who is being missed? Inside the DRC’s Ebola response, shortages, strained treatment centers, and gaps in community trust reveal a more complicated story.
By Michelle Gardner
Duringthe past, indiscriminate use of antibiotics has given once-susceptible bacteriathe chance to develop defenses against antibiotics, thus providing theopportunity for resistant strains to flourish. Reports of vancomycin-resistant enterococcus(VRE) and methicillin-resistant Staphylococcus aureus (MRSA) haveincreased in oncology units of large teaching hospitals, and nursing homes,long-term care facilities, and community hospitals, respectively.
Both Enterococci and Staphylococcus are part of the body'snormal flora, which is considered "good" bacteria and essential forhuman health.4 But if the body's natural defense system breaks down (i.e.,after an invasive procedure, trauma, or chemotherapy), these normally benignbacteria can invade tissue, proliferate, and cause infection.
At one time, enterococcal infections were easily treated with high doses ofpenicillin or ampicillin, which progressed to aminoglycosides, then vancomycin.Many clinicians suspect that over reliance on vancomycin led to the developmentof VRE, which isn't easily treated with any antibiotic.
Who's at risk?
Patients most at risk for VRE include, but are not limited to,immunosuppressed patients or those with severe underlying disease; elderlypatients, especially those who've had prolonged or repeated hospital admissions;patients with wounds with an opening to the pelvic or intra-abdominal area,including surgical wounds, burns, and pressure ulcers; and patients exposed tocontaminated equipment or to a VRE-positive patient.
According to the Centers for Disease Control and Prevention (CDC), infectedpatients carry VRE and show clinical signs or symptoms of disease. Colonizedpatients carry VRE but do not have clinical signs or symptoms of infection.Patients are usually colonized in the gastrointestinal tract and occasionally inthe urinary tract. The goal of screening is to identify as many colonizedpatients as possible so that infection control measures can be implemented todecrease transmission and reduce the number of patients infected with VRE.
VRE is spread through direct contact between patient and caregiver, orpatient to patient. It also can be spread through patient contact withcontaminated surfaces. VRE has been detected on patient gowns, bed linens, andhandrails.
Understanding MRSA
Patients most at risk for MRSA include immunosuppressed patients, burnpatients, intubated patients, and those with central venous catheters, surgicalwounds, or dermatitis.
Risk factors include prolonged hospital stays, extended therapy with multipleor broad-spectrum antibiotics, and close proximity to those colonized orinfected with MRSA.
Like VRE, MRSA enters health care facilities through an infected or colonizedpatient or colonized healthcare worker (HCW). Although MRSA has been recoveredfrom environmental surfaces, it's transmitted mainly on HCWs' hands. Typically,MRSA colonization is diagnosed by isolating bacteria from nasal secretions as40% of adults and most children become transient nasal carriers.
The following guidelines apply when caring for a patient with MRSA or VRE:
More bad bugs
Besides MRSA and VRE, antibiotic-resistant organisms continue to appear:
S. aureus intermediately resistant to vancomycin (known by the acronymVISA). To prevent the rise of VRSA and other antibiotic-resistant organisms, usesimilar techniques for preventing the spread of VRE and MRSA. Among the mostimportant measures: good hand washing, barrier precautions, and continuedvigilance against the spread of these organisms.